Women’s Mental Health & Trauma Recovery: What Residential Treatment Really Offers
For many women, the breaking point doesn’t arrive all at once. It builds quietly — through years of unprocessed trauma, chronic anxiety, burnout, or a slow slide into substance use as a way to cope. By the time someone starts searching for help, they’re often looking for more than a weekly therapy appointment. They’re looking for a place that can hold the whole picture: the mind, the body, and the life that needs rebuilding.
This is where women’s residential mental health and trauma treatment centers come in — programs like Villa Kali Ma in California, and others like it across the country, that offer immersive, live-in care specifically designed around how women experience trauma, addiction, and recovery differently than men do.
If you’re researching these programs for yourself or someone you love, here’s what to actually know before you choose one.
Why Women-Only Treatment Programs Exist
Trauma doesn’t show up the same way for everyone. Research consistently shows that women are more likely to have experienced interpersonal trauma — abuse, assault, or complex relational wounds — and are more likely to develop co-occurring anxiety, depression, or eating patterns alongside substance use. Mixed-gender treatment settings can sometimes recreate the very dynamics — power imbalances, unsafe attention, difficulty being vulnerable — that contributed to the trauma in the first place.
Women-only residential programs are built to remove that barrier. The goal isn’t exclusion; it’s creating a setting where someone can actually let their guard down enough to do the deeper work.
What These Programs Typically Include
Most reputable women’s residential mental health and trauma centers combine several layers of care rather than relying on one method alone:
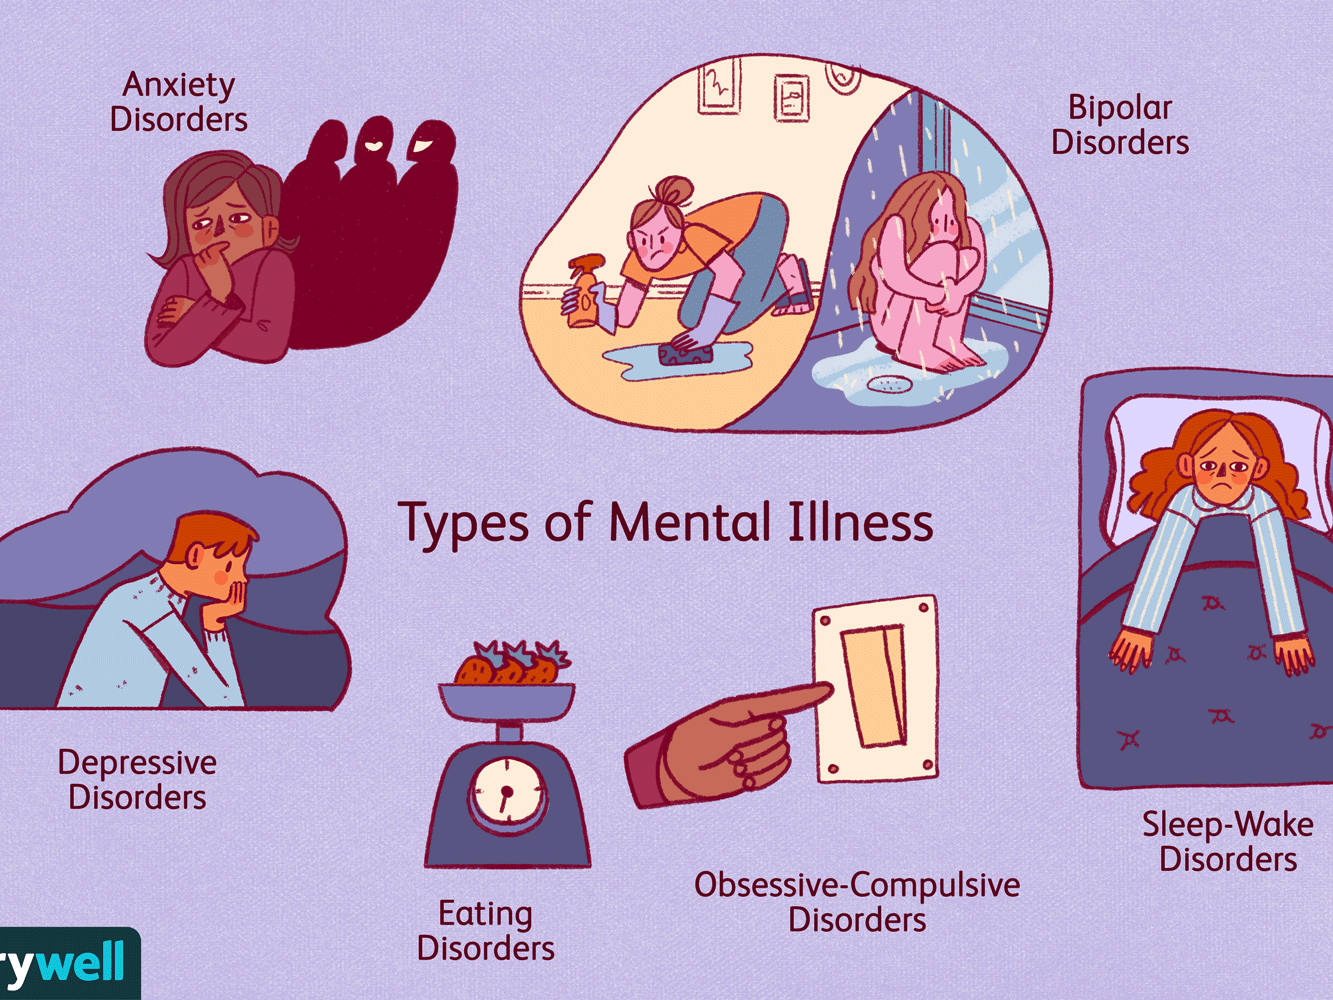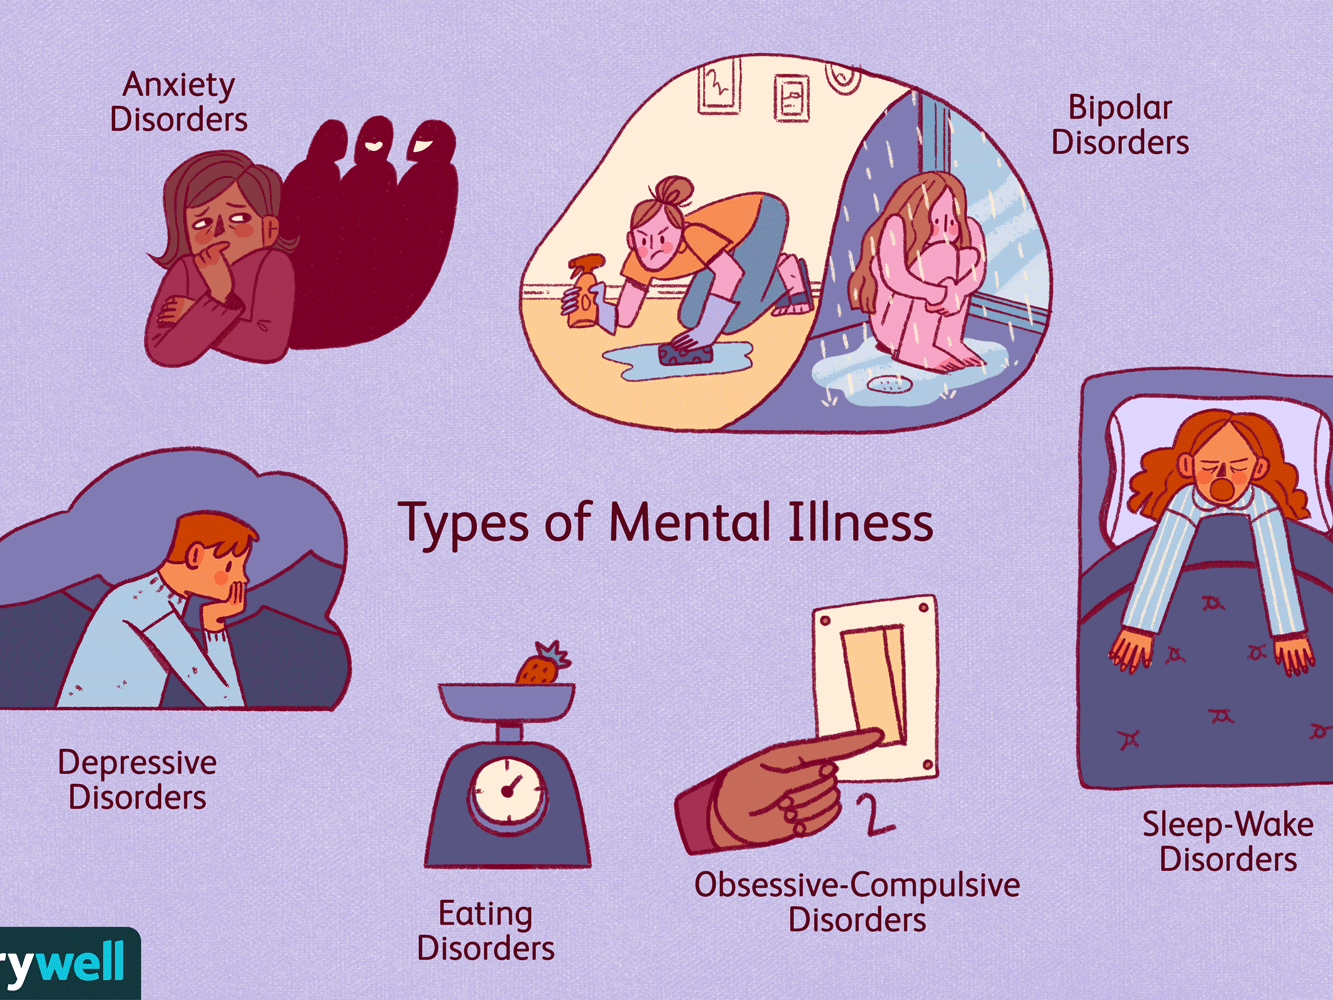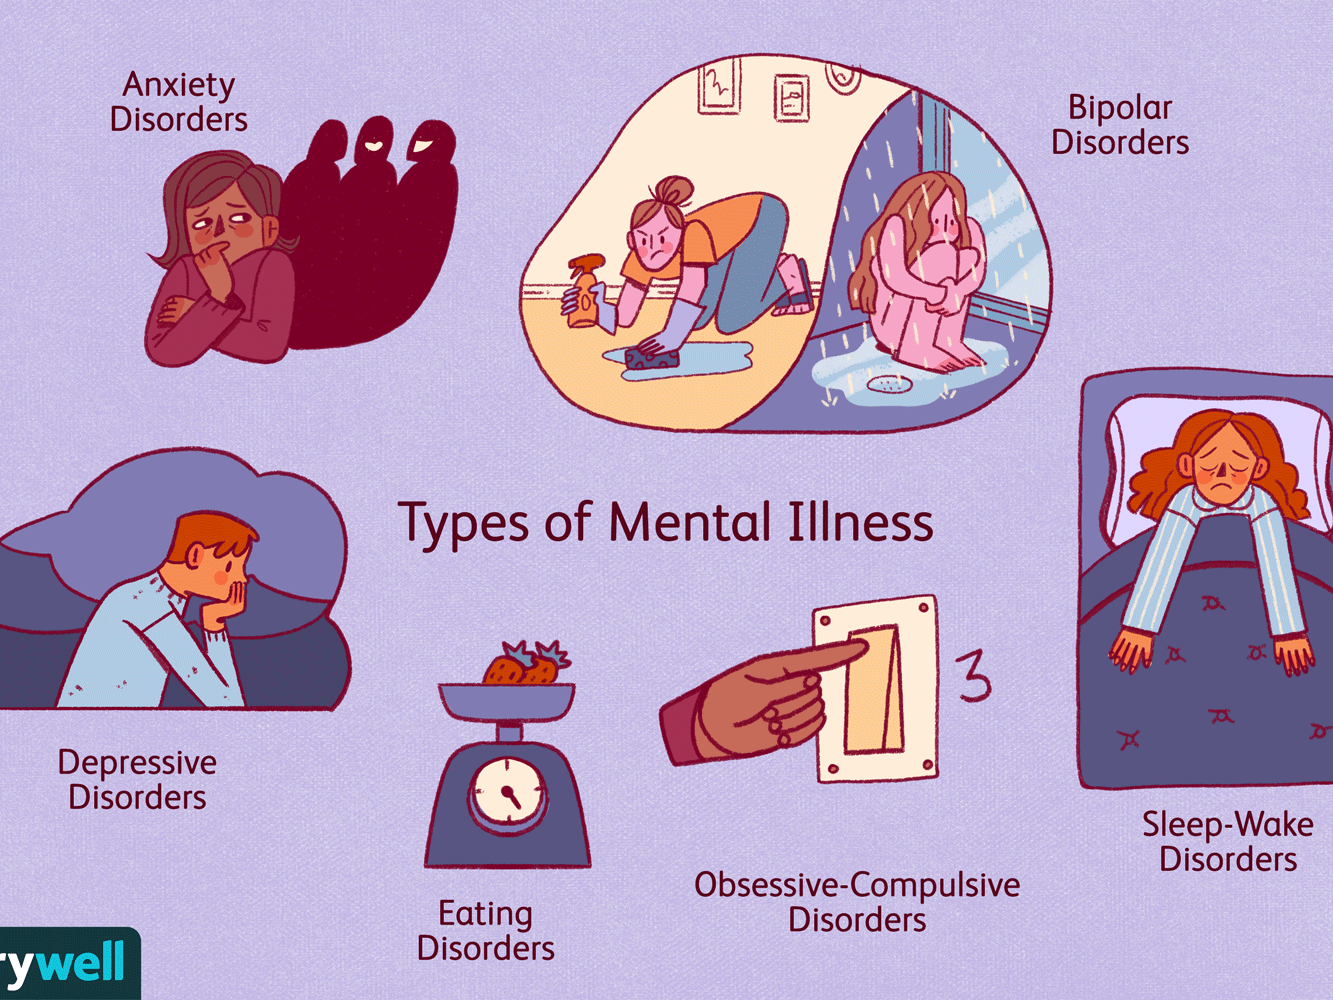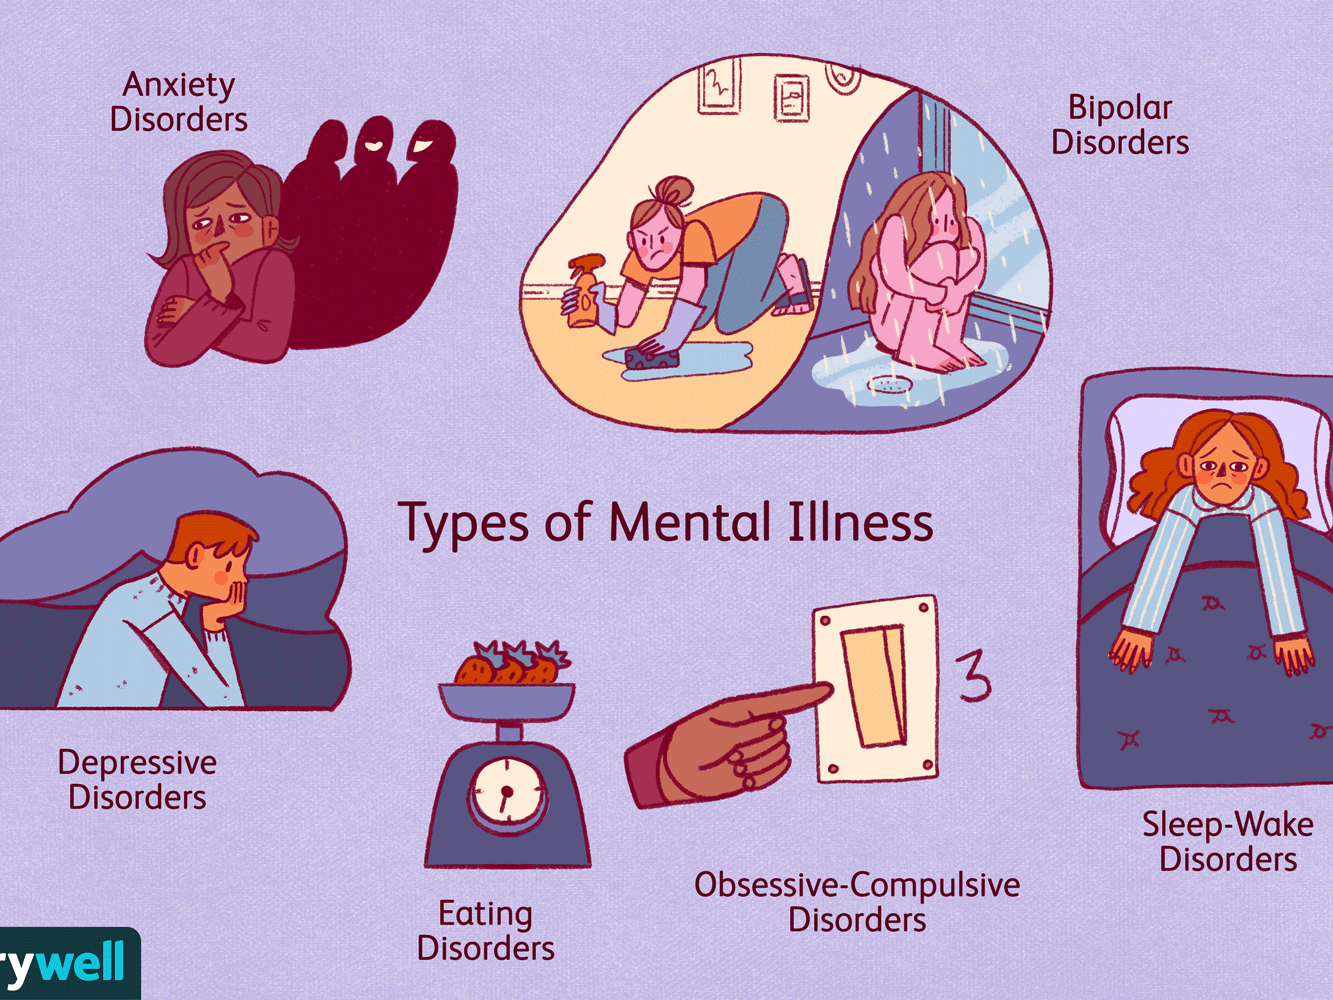
Clinical mental health treatment Licensed psychiatrists and therapists assess and treat co-occurring conditions — PTSD, anxiety, depression, and substance use disorders together, not in isolation. This is often called a “dual diagnosis” or “co-occurring disorders” approach, and it matters because treating addiction without treating the underlying trauma rarely holds long-term.
Somatic and body-based therapy Talk therapy alone often isn’t enough when trauma is stored in the nervous system, not just in memory. Many programs use somatic release work, nervous system regulation techniques, and body-based practices to help process trauma that words can’t fully reach.
Holistic and experiential practices Yoga, breathwork, art or movement therapy, and time in nature are common additions — not as a replacement for clinical care, but as a way to help the body reconnect with a sense of safety.
Structured community Living alongside other women going through similar struggles, in a home-like rather than clinical setting, is often cited by former residents as one of the most meaningful parts of recovery — the sense of not being the only one.
Aftercare and stepped-down support Good programs don’t end at discharge. They typically offer outpatient step-down options (like an Intensive Outpatient Program, or IOP) and connect residents to ongoing support groups so recovery doesn’t stop the moment treatment does.
Questions to Ask Before Choosing a Program
If you’re comparing options — whether it’s a well-known name like Villa Kali Ma or a smaller local program — these are the questions worth asking directly:
- Is the facility licensed by the state’s Department of Health Care Services (or equivalent)? Ask for the license number.
- Who is overseeing medical and psychiatric care — is there a licensed physician or psychiatrist on staff, not just counselors?
- Does the program treat co-occurring conditions (trauma + addiction, or trauma + anxiety/depression) together, or only one at a time?
- What does a typical day actually look like — how much is clinical therapy versus holistic/experiential work?
- What insurance plans are accepted, and what happens if coverage runs out before treatment is complete?
- What does aftercare look like once residential treatment ends?
- Can you speak to the intake team before committing, and can family be involved in the process if appropriate?
A program that’s confident in its care will answer these clearly and without pressure tactics.
A Note on Cost and Insurance
Residential mental health and trauma treatment is a significant financial and time commitment — often 30 days or more, and not always fully covered by insurance. Many centers, including larger names in this space, work with major insurers (such as Health Net-affiliated plans) as in-network or out-of-network providers. Before enrolling anywhere, get a clear, written breakdown of what’s covered, what isn’t, and what the total out-of-pocket cost could look like.
You Don’t Have to Have a “Big Enough” Reason
One of the most common things women say after starting treatment is that they waited too long because they didn’t think their pain was “bad enough” to deserve help. Trauma isn’t a competition, and burnout, chronic anxiety, and quiet substance dependence are just as valid reasons to seek residential-level care as a single dramatic crisis point.
If you’re not sure whether your situation calls for residential treatment versus outpatient therapy, that’s a conversation worth having with a licensed mental health professional rather than deciding alone.
This article is for general educational purposes and isn’t a substitute for professional medical or psychiatric advice. If you or someone you know is in immediate crisis, please contact a local emergency service or a crisis line such as the 988 Suicide & Crisis Lifeline (call or text 988 in the US).
Created by you


Add PDFs, documents, or other text to reference in this project.